











Couples Therapy in Madrid: How to Choose the Right Clinic and What to Expect
Summary
Couples therapy provides a safe space to understand conflict, improve communication, and rebuild connection. This article explains when to seek support, what sessions involve, typical duration and costs in Madrid, which qualifications to look for in a therapist, and how to choose between in-person and online therapy according to each couple’s needs.
Relationships sometimes go through periods of crisis, which are a natural part of any long-term bond. During these moments, it can be easy to fall into negative patterns that feel difficult to break without support. In some cases, unresolved wounds may also remain present in the relationship, continuing to affect the connection over time. Seeking professional help can therefore be one of the most effective ways to address these difficulties and rebuild a healthier, more secure way of relating to one another.
However, choosing the right clinic and therapist to begin this process is not always easy. For this reason, this article aims to help you make an informed decision that fits your needs as a couple.
What is couples therapy?
Couples therapy is a safe space where you can pause the pace of everyday life and calmly explore what is happening in your relationship and how each of you is feeling within it. With the support and guidance of the therapist, you are encouraged to express yourselves openly, listen to one another in a different way, and begin building healthier patterns of interaction that help you feel closer and better understood.
It is important to remember that nobody is born knowing how to navigate and manage the complexities of relationships. Emotional dynamics within a couple can sometimes feel overwhelming or confusing, and asking for help during difficult moments is both natural and a healthy, courageous way of caring for the relationship.
Throughout the process, the therapist will help you identify recurring cycles and patterns that may create distance, conflict, or disconnection, and work with you to transform them into more supportive and constructive ways of relating. Over time, you will also develop practical tools to improve communication and manage the intense emotions that can arise during disagreements or challenging moments.
The goal of therapy is to help you build a relationship in which both partners feel seen, valued, emotionally supported, and understood. Together with the therapist, you will work towards reconnecting and creating a bond that feels lighter, closer, and more fulfilling.

Regarding the structure of the process, sessions usually last around 60 minutes and are generally held weekly at the beginning of therapy. As progress is made and changes begin to consolidate in daily life, sessions are gradually spaced out according to your needs and the stage your relationship is in.
The therapeutic process often combines joint sessions with individual sessions. This allows the work to focus not only on the couple’s dynamic itself, but also on each partner’s personal history, as the way we relate to others is often influenced by past experiences, emotional learning, and attachment patterns developed throughout life. Our past can shape the small things that trigger us in relationships, as well as the way we interpret, react to, or manage conflict. Family history, emotional wounds, and unmet emotional needs frequently play an important role in how we connect with one another.
As for the duration of therapy, every couple moves at their own pace, so there is no exact timeline that applies to everyone. On average, the process tends to last between 6 and 10 months. In some cases, therapy may be shorter and more focused, while in others it may involve deeper and longer-term work, depending on the challenges involved and the goals you wish to address.
Beyond the specific duration, therapy can become a space of support, care, and guidance that you can return to whenever life presents new challenges or when you feel the need to reconnect, better understand each other, and strengthen your bond from a more conscious and secure place. Couples therapy is not about blame or judgment, but rather about understanding what is happening within the relationship and building together a healthier, more satisfying, and more meaningful way of relating.
Couples Therapy Prices in Madrid: How Much Does It Cost?
- The location of the clinic within Madrid.
- The therapist’s level of experience and training.
- Whether sessions are offered in a foreign language.
- The duration of the sessions.
- Whether therapy is provided online or in person.
As a general guideline, the average cost of couples therapy in Madrid ranges between €90 and €140 per session.
When Should You Consider Couples Therapy?
- Conflicts escalate to the point where both of you feel emotionally exhausted and increasingly distant from one another.
- You feel trapped in a negative cycle in which almost anything said or done is misunderstood or interpreted negatively.
- There are unresolved wounds in the relationship that still feel emotionally present.
- Arguments follow repetitive negative patterns and you struggle to reach resolutions that truly feel settled.
- You feel unheard, misunderstood, or emotionally neglected within the relationship.
- Sexual intimacy is not working well or no longer feels satisfying.
- You notice that you have stopped enjoying quality time together.

How to Find a Good Couples Therapist in Madrid
- Is officially registered with the Official College of Psychologists of Madrid.
- Holds the required clinical qualifications, such as a Master’s Degree in General Health Psychology or equivalent clinical training.
- Has specific training in systemic therapy, focused on relational dynamics and relationship functioning.
- Has specialised training in couples therapy, ideally with recognised certifications such as those from the Gottman Institute or Emotionally Focused Therapy (EFT).
- Has experience working with couples and, in the case of international couples, is comfortable working in multicultural contexts and ideally in different languages.
It is also important that, during your first session together, you both feel comfortable with the therapist and their way of working. Feeling safe, understood, and connected with the therapist is an essential part of building a successful therapeutic process.
Where to Find a Couples Therapy Clinic in Madrid
When looking for a couples therapy clinic, the most important factor is the therapist’s level of training and specialisation. However, it is also helpful to consider practical aspects such as the clinic’s location and accessibility, as choosing a convenient location can make it easier to maintain consistency throughout the process.
It is equally important to think about which format best suits your needs and lifestyle — whether online or in-person therapy — as well as ensuring that the therapist’s availability, schedule, and language options are compatible with your circumstances.
To make your search more reliable and accurate, you may also consult trusted sources such as the website of the Official College of Psychologists or seek recommendations from other couples who have gone through a similar process.

In-Person vs Online Couples Therapy
Nowadays, more and more therapists are highly experienced in working online, which means that both in-person and online couples therapy can be equally effective and satisfying. However, in-person sessions may offer an additional experiential component that, for some couples, can help foster a greater sense of connection, engagement, and commitment to the therapeutic process.
Frequently Asked Questions (FAQ)
1. When is couples therapy recommended?
It may be helpful when conflicts repeatedly create distance, unresolved issues continue to affect the relationship, partners feel unheard or misunderstood, sexual difficulties arise, or shared enjoyable moments have decreased.
2. How long are couples therapy sessions and how long does therapy usually last?
Sessions typically last around 60 minutes and are usually weekly at the beginning. The overall duration varies for each couple, although the article gives an approximate average of 6 to 10 months.
3. How much does couples therapy cost in Madrid?
As a general guide, sessions usually cost between €90 and €140. Prices may vary depending on the therapist’s training, location, language, session length, and whether therapy is in person or online.
4. How should you choose a couples therapist in Madrid?
Look for appropriate professional registration, relevant health or clinical qualifications, specific training in systemic and couples therapy, and experience working with couples. Language skills and multicultural experience may also be important.
5. Is in-person or online couples therapy better?
Both formats can be effective and satisfactory options. In-person therapy may provide an additional experiential component, while the most suitable format depends on the couple’s needs, availability, and lifestyle.
About the author
Alex Baley

Division of Psychology, Psychotherapy and Coaching
Psychologist
Adults, families and couples
Languages: English and Spanish


How to Stop Taking Antidepressants?
Summary
Stopping antidepressants requires medical planning, gradual tapering, and follow-up. The decision depends on diagnosis, course, and life context. Abrupt discontinuation may cause withdrawal symptoms. Distinguishing these from relapse is essential, as is strengthening healthy habits and psychological support to maintain emotional stability during the process.
Stopping an antidepressant is not simply a matter of “stopping a pill.” It is a complex process: medical, psychological, and personal, that should be approached with planning, information, and professional support.
In my clinical practice, this is one of the questions I hear most often: “Doctor, how long do I need to take it?” or “How can I stop it without feeling worse?” In this article, I would like to explain in a clear and approachable way what you should know before discontinuing an antidepressant, how to do it safely, and which signs to watch for during the process.
The first question we need to ask is whether it is truly the right time to stop. Not every moment in life is suitable for discontinuing treatment. The decision depends not only on how long you have been taking the medication, but also on several other factors:
- The initial diagnosis (mild, moderate, or severe depression, anxiety disorder, OCD, etc.).
- Whether this is your first episode or if there have been previous relapses.
- How long you have remained stable without symptoms.
- Your current level of stress (for example, during an exam period or a difficult winter).
- Whether you have psychological support in place.
As a general guideline, always to be individualized, we usually recommend continuing treatment for six to twelve months after full recovery following a first depressive episode. In cases of previous relapses or more severe conditions, treatment may need to be maintained for longer. Stopping too early increases the risk of relapse. It is also important to remember that the feeling of “I’m fine now” often appears precisely because the treatment is working.
Antidepressants do not cause addiction in the classical sense, but they do lead to neurobiological adaptation. The brain adjusts to the presence of the medication. For this reason, in most cases they should not be stopped abruptly. When they are suddenly discontinued (either because the medication runs out or because someone decides to stop on their own) what is known as antidepressant discontinuation syndrome may appear (see our blog article on this topic). This is not dangerous in itself, but it can be very uncomfortable.
The most common symptoms include dizziness, nausea, a sensation of electric shocks in the head (“brain zaps”), irritability, anxiety, sleep disturbances, or flu-like symptoms. Some antidepressants cause more withdrawal symptoms than others, especially those with a shorter half-life. This is why the discontinuation plan must always be tailored to both the specific medication and the individual patient.

How to do it?
Discontinuation is done gradually and step by step. There is no single schedule that works for everyone, but the general principle is to reduce the dose progressively and observe how the body responds. In many cases, we reduce the dose by 10–25% every two to four weeks. For example, someone taking 20 mg may reduce to 15 mg for a few weeks, then to 10 mg, then to 5 mg, and finally stop. Sometimes this means cutting tablets into halves or quarters to allow for smaller reductions. In treatments that have lasted several years, even slower reductions may be advisable. If symptoms appear, it does not mean that stopping the medication is impossible, it may simply mean that we need to proceed more slowly.
A frequent question during this process is how to distinguish withdrawal symptoms from a depressive relapse.
Withdrawal symptoms typically appear a few days after reducing the dose and improve quickly if the dose is increased again. They often include noticeable physical symptoms such as dizziness or “brain zaps.”
A relapse, on the other hand, tends to develop more gradually and resembles the original episode: persistent sadness, loss of interest, apathy, feelings of guilt, and difficulty experiencing pleasure.
Distinguishing between these two situations is crucial in order not to misinterpret a temporary physiological reaction as the return of the illness.
As we know, psychopharmacological treatment is a form of support—like a temporary crutch. It does not act in isolation but is part of a broader set of measures: psychotherapy, healthy lifestyle habits, social support, and self-care. When combined, these approaches can produce positive and lasting results over time. Stopping an antidepressant is therefore not only about reducing milligrams. It is also an opportunity to strengthen the foundations that support emotional and mental stability.
During this period it is helpful to reinforce healthy habits: maintaining regular sleep routines, keeping consistent daily schedules, engaging in regular physical activity, spending time in natural daylight, and, if possible, continuing or beginning psychotherapy. Physical exercise, for example, has well-documented antidepressant effects. It does not always replace medication, but it can significantly help prevent relapse. Discontinuation should always be accompanied by a broader focus on overall mental health.
Many people feel anxious or apprehensive about stopping their medication. This is completely normal. For some, the antidepressant was a lifeline during a very difficult period, when other resources were no longer sufficient. Letting go of it may create a sense of insecurity, as if giving up a safety net. In these situations, it is important to distinguish between psychological reassurance and a genuine clinical need for long-term treatment. There is nothing negative about needing medication for an extended period if it is clinically indicated. Nor is there anything heroic about stopping it prematurely.
There are situations in which we recommend particular caution when considering discontinuation:
- Severe depression with previous suicidal ideation.
- Recurrent depressive disorder.
- Bipolar disorder.
- Long-standing severe anxiety.
- Significant family history of mood disorders.

In such cases, discontinuation must be planned very carefully, and in some situations it may not be advisable to stop treatment completely.
An interesting fact that often surprises patients is that the brain may take longer to adapt to stopping an antidepressant than it does to starting one. Many people notice improvement within a few weeks when they begin treatment, but the full neurobiological adjustment is more complex. Similarly, when reducing the dose—especially during the final steps, such as going from 5 mg to zero—the nervous system may react more strongly than during earlier reductions. This is why the final stages often require particular patience.
What happens if, during the discontinuation attempt, we observe a clear and sustained return of depressive symptoms, significant functional impairment, persistent insomnia, or intense anxiety that interferes with daily life?
In these cases, we do not speak of failure, but rather of important clinical information. It may simply mean that the timing is not yet right. Some people need several attempts before they can discontinue treatment completely. Others discover that a very small maintenance dose provides stability with minimal side effects. That, too, can be a valid option.
What I never recommend is stopping medication without consulting your doctor, reducing the dose abruptly because “I feel fine now,” comparing your experience to that of others, or compensating for withdrawal with alcohol or other substances.
Can people live without antidepressants?
Yes, of course—many people do. However, depression can sometimes be a recurrent illness. Maintaining treatment when indicated is not a sign of weakness but a form of prevention. It can be compared to other chronic conditions: if someone needs medication to control blood pressure or insulin for diabetes, they do not see it as a personal failure. Mental health should be viewed in the same way. It is also reassuring to know that if an antidepressant has helped in the past, it remains a resource that can be used again should another depressive episode occur.
If you are considering stopping your antidepressant, my recommendation is to do so together with your doctor, with a clear plan and proper follow-up. As you can see, there is flexibility and many possible ways to approach this process while respecting both your psychological and physical well-being. The goal is not to take medication longer than necessary—but neither is it to stop before you are ready. A well-planned discontinuation is gradual and respectful of both your brain and your personal history. It is a clinical decision that should be made with information, caution, and support.

Frequently Asked Questions (FAQ)
1. When is the right time to stop antidepressants?
It depends on diagnosis, clinical stability, and stress levels. Typically, 6–12 months after full recovery is recommended.
2. Can antidepressants be stopped abruptly?
No. Sudden discontinuation may cause withdrawal symptoms such as dizziness, anxiety, or insomnia.
3. How should antidepressants be tapered?
Gradually, reducing the dose by 10–25% every 2–4 weeks, tailored to the individual.
4. How can withdrawal be distinguished from relapse?
Withdrawal appears quickly with physical symptoms; relapse is gradual and mirrors prior depressive symptoms.
5. Is psychological support necessary?
Yes, it helps prevent relapse and strengthens emotional coping strategies.
About the author
Dr. Alma Moser is a child and adolescent psychiatrist at Sinews. She specializes in depressive and anxiety disorders and works with children, adolescents, and adults. She also treats other conditions such as ADHD, addictions, autism spectrum disorders, and obsessive–compulsive disorder. She has worked with children in outpatient settings, day hospitals, and inpatient units.

Division of Medicine
Psychiatrist
Children, adolescents and adults
Languages: English, German, French and Spanish

Stress vs. Anxiety: A Practical Guide for Everyday Life
Summary
This article explains the differences between stress and anxiety, their physiological similarities, and how to identify them. Stress relates to present demands, while anxiety anticipates future threats. It outlines when they become problematic and provides practical strategies to manage them, promoting emotional balance and overall well-being.
Is what I’m feeling stress or anxiety? Could it be both? Does it really matter to know the difference? What can I do to manage stress? And what about anxiety?
These are the questions we will explore in this article. The goal is to increase awareness of these experiences and help you better understand what you may be going through. When you are able to recognize when you are feeling stressed or anxious, it becomes easier to manage these responses more effectively.
Many people use the terms stress and anxiety interchangeably, because they are emotional responses that share many similarities. However, there are also important differences between them that are worth knowing about.
Defining Stress and Anxiety
Let’s start by defining stress and anxiety in a clear and practical way.
Stress can be understood as the response our body and mind have to a situation that we perceive as a challenge or a threat (what psychologists often call a stressor). When we perceive something as challenging or threatening, changes occur both at a physiological level (for example, an increased heart rate) and at a psychological level (such as heightened alertness). These changes prepare us to deal with the situation. The triggers can vary widely—a work deadline, an exam, an interpersonal conflict, or an overload of tasks—but the body’s response tends to be quite similar.
At moderate levels, stress can actually be helpful because it keeps us alert and ready to act when needed. In fact, psychologists Robert M. Yerkes and John Dillingham Dodson proposed that moderate levels of stress (or arousal) allow us to achieve optimal performance. Too little stress can reduce performance, while too much stress can also impair it.
Anxiety can also be defined as a response of the body and mind, but it usually occurs when we anticipate a future or hypothetical situation that we perceive as threatening. Sometimes it may arise without the person being fully aware of what triggered it (for example, which specific thought or anticipation caused it).
In his book Why Zebras Don’t Get Ulcers, Robert M. Sapolsky describes anxiety as a kind of “physiological commotion without an apparent cause.” From the outside, nothing seems to be happening, but in the person’s mind the sense of threat is very real.
Sometimes you may not even know why you are feeling anxious. You may experience it as this kind of “physiological commotion without an apparent cause”, too. You are aware that you feel anxious, but you are not consciously thinking about or anticipating anything specific, nor can you connect it to something that is happening at that moment.
There are at least two reasons why this can happen. The first is that not everything we perceive becomes conscious. Our nervous system constantly detects subtle or ambiguous signals that might indicate danger, and these signals do not always reach conscious awareness. As a result, you may notice that your body feels activated without knowing exactly why.
Another reason is that people sometimes become aware of their anxiety when they finally find themselves in a calm environment with few external stimuli. Imagine, for example, that Ana arrives home from work after a particularly long day filled with meetings, an important deadline, and several smaller tasks. When she finally lies down on her sofa, she begins to notice that her heart is beating very fast, but she does not understand why. In this case, Ana is noticing her heartbeat for the first time that day. In the quiet of her home, with nothing else demanding her attention, she becomes aware of a psychophysiological response that was likely present throughout her busy day.
In this sense, anxiety can be seen as a general alarm signal that something may require our attention. It might relate to a future situation we need to prepare for, an experience that affected us but went unnoticed at the time (for example, an interaction with a colleague or family member), or simply a sign that we are in a state of heightened alertness without realizing it.

Key Similarities and Differences
Stress and anxiety share a common physiological and psychological response. Both involve activation of the sympathetic nervous system, which produces what is known as the fight-or-flight response. The heart beats faster, blood flows to the muscles in the arms and legs to prepare the body for action, and breathing speeds up to deliver more oxygen to the bloodstream so the muscles have more energy.
These responses helped our ancestors survive by enabling them to escape from danger or confront threats effectively. Although our lives have changed and the dangers we face today are less immediate—we are no longer running from predators—our nervous system still activates the same biological response.
In fact, when we imagine threatening situations, our nervous system can trigger the same fight-or-flight response as when we encounter a real threat in the present, although usually to a lesser degree. Whether we are facing something stressful in the moment or simply imagining it, the body’s response can be very similar.
The main difference between stress and anxiety lies in the type of trigger.
Stress is usually related to demands or threats in the present that we can identify relatively clearly. Anxiety, on the other hand, is typically connected to threats that are anticipated, future-oriented, or more diffuse.
One way to understand this difference is to think about animals. Animals can experience stress, but it is much less likely that they will experience anxiety in the same way humans do, because they do not have the same capacity to imagine or predict the future. This ability is extremely useful for humans, but it can also make us more vulnerable to sustaining the fight-or-flight response for longer periods—even after the immediate danger has passed—leading to worry or chronic stress.

When Do Stress and Anxiety Become a Problem?
A basic way to determine whether stress or anxiety is becoming problematic is to ask whether it interferes with your daily life—whether at work, in your studies, or in your personal, social, or family life.
For example: Are you able to function normally in your social life? Is it becoming harder than before to cope with work or academic demands?
It is also important to consider frequency, duration, and intensity. Do you feel overwhelmed frequently? How long do these moments of stress or anxiety last? How intense are your symptoms?
If they occur constantly, take a long time to subside, or make it difficult for you to carry out your daily activities, they may become problematic.
Another important question is whether the intensity of the response fits the situation. Does your reaction feel proportionate to what is happening, or does it seem excessive? If the level of stress or anxiety feels disproportionate to the situation, it may be a sign that it is becoming problematic.
It is helpful to distinguish between adaptive stress and anxiety—which tend to be occasional and temporary—and chronic stress or maladaptive anxiety, which are more persistent and may require attention. The goal is not to eliminate these emotions, but to recognize whether they remain within a healthy range that you can manage, or whether you are spending too much time feeling overwhelmed by them.
We know that chronic stress and persistent anxiety can affect both physical and psychological health. They can also create a vicious cycle. When we feel stressed or anxious, we tend to sleep worse, digest food less efficiently, and make less healthy decisions (for example, smoking or avoiding exercise). These factors can in turn make us more vulnerable to stress and anxiety.
For this reason, it is worth trying to keep stress and anxiety within a manageable and healthy range.

What Can I Do?
You might be wondering: What can I do to manage these emotional responses? How can I prevent chronic stress? How can I manage my anxiety?
Everyone copes with stress and anxiety in different ways. Some strategies work better for some people than for others. The best way to find out what works for you is to try different approaches and adapt them to your own circumstances.
Here are some general strategies that can help manage both stress and anxiety.
General strategies for coping with stress and anxiety
- Take care of your body to support your mental well-being. Regular physical exercise (including gentle exercise), adequate sleep, a balanced diet, and avoiding substances can all make a difference.
- Pay attention to when you feel stressed or anxious and how intense the feeling is. When we are not aware of how stressed or anxious we are, we may push ourselves too far and fail to take necessary steps to manage these emotions, such as taking a break, giving ourselves time, or delegating tasks.
- Reflect on what is within your control and what is not. A well-known phrase captures this idea: “God, grant me the serenity to accept the things I cannot change, the courage to change the things I can, and the wisdom to know the difference.” Recognizing this distinction helps us direct our energy toward what we can actually influence. When problems have no solution, it may be more helpful to reframe them, to try to accept them or limit how much attention we give them. Not making this distinction can lead to unnecessary frustration and stress.
- Maintain a supportive social network. Social connection is strongly linked to better physical and emotional health throughout life and acts as a protective factor against stress and anxiety. Make sure you spend time with people who matter to you and try to avoid isolating yourself.
Strategies specifically for managing stress
- Evaluate the demands you are facing and the resources you have available. Stress often arises when demands exceed our resources—such as time, energy, skills, or support. Consider whether your current abilities or circumstances allow you to meet those demands. If not, it may be helpful to reduce expectations or avoid taking on additional demands.
- Manage your resources by prioritizing, organizing, and delegating. In other words, choose your battles. Remember that you do not have to do everything—at work, at home, or in your personal life. Ask for help when needed and practice saying “no” when you do not have the time or energy to commit to more responsibilities.
- Build real breaks into your schedule whenever possible. To prevent your nervous system from remaining chronically activated, it is important to plan periods of rest that allow you to return to a calmer state.
Strategies specifically for managing anxiety
- Practice mindfulness. Mindfulness can help you observe your thoughts without automatically treating them as facts. This counters our natural tendency to react to thoughts as though they reflect reality. If you are new to mindfulness, it can be helpful to learn with a qualified instructor who can guide you and adapt the practice to your needs and circumstances.
- Identify and work on your thinking patterns. Since anxiety is often triggered by anticipation and thoughts, it can be useful to notice the types of thoughts you tend to have and examine them more closely. We often fall into thinking traps, such as catastrophic or overly rigid interpretations of reality. To challenge these patterns, practice asking yourself questions such as: “Is what I’m thinking realistic?”, “What evidence supports this idea?”, and “How likely is this outcome that I’m imagining, really?”
- Distinguish between unproductive worry and problem-solving. Research shows that when people worry repeatedly, they may feel a greater sense of control over a stressful situation—even when that control is illusory. Thinking can be useful when it helps us solve problems, but repetitive worry often does not lead to solutions and may increase stress over time. Excessive worry can become a habit, and while it is not always easy, it is possible to learn not to feed that habit. When you notice yourself worrying, ask: “Is thinking about this helping me?” or “Am I moving toward a solution?”
- Practice allowing uncomfortable emotions to be present. When someone becomes caught in a cycle of worry and worrisome trains of thoughts, they may gain a temporary sense of control while also avoiding the direct experience of anxiety. When we allow the emotion to be present without holding on to these worry thoughts, it can follow its natural course and gradually fade.
- Gradually face what you fear—when it is safe to do so. Avoiding situations that trigger anxiety can make the anxiety grow stronger over time. Approaching what you fear step by step (for example, speaking in public) can help you realize that it is not as dangerous as it seems and that you are capable of coping with it. In some cases, doing this with the support of a professional can be especially helpful.

Some people find it difficult to apply these strategies, may not know how to implement them, or may feel that they do not work for them. If stress or anxiety is affecting your daily functioning or overall well-being, a mental health professional can help you better understand what you are experiencing and find strategies tailored to your situation.
Stress and anxiety are similar responses that can be both helpful and harmful depending on their intensity and frequency. Stress helps us respond to present demands, while anxiety helps us anticipate potential future threats or signals that something may require our attention. The goal is not to eliminate these emotions entirely, but to learn to recognize when they are helping you and when you may need to intervene, so they do not interfere with your life, your health, and your well-being.
Frequently Asked Questions (FAQ)
1. What is the difference between stress and anxiety?
Stress responds to identifiable present demands, while anxiety anticipates future or unclear threats.
2. Can I experience both at the same time?
Yes, they can coexist and share similar physical symptoms.
3. When do they become problematic?
When they interfere with daily life or are intense, frequent, or disproportionate.
4. How can I manage stress and anxiety?
Through self-care, organization, social support, mindfulness, and cognitive strategies.
5. Should I seek professional help?
Yes, if they impact daily functioning or cause persistent distress.
About the author
Sofía Salgado is a clinical psychologist at Sinews. She works with adolescents and adults and conducts psycho-educational assessments. She addresses issues such as anxiety, depression, emotional dysregulation, and problems related to self-esteem or personality. She provides support during periods of adjustment, grief, and interpersonal relationship difficulties, among other issues. Her approach is humanistic and integrates tools and techniques from other schools of thought based on each patient’s needs, thanks to her training in cognitive-behavioral therapy and third-generation therapies.

Sinews MTI
Psychology, Psychiatry and Speech Therapy

Sexual myths damage your mental health (and you may not have known it)
Summary
Sexual myths can impact self-esteem, anxiety, and relationship quality. Beliefs such as constant desire, orgasm as the goal, or love guaranteeing good sex may lead to guilt and frustration. Accurate sex education, open communication, and professional support are essential for a healthier and more emotionally balanced sexual life.
Talking about sex with family, friends, or simply in public is still uncomfortable, if not taboo, in many cases, and when it is discussed, it is often full of myths, made-up stories, and false beliefs that affect how we experience intimacy. But what many people don’t realise is the huge psychological impact these myths can have, which is often reflected in therapy: anxiety, guilt, low self-esteem… Do those sound familiar?
In this article, we will try to debunk some of these myths that we encounter in popular discourse, understand where they come from and, above all, see how they can damage our emotional and sexual well-being. Because the most important thing for a healthy and fulfilling sex life is to be well informed.
Myth 1: ‘Men have an insatiable and unconditional desire for sex.’
This belief is one of the classics in popular ideology. The idea that male desire is constant and inexhaustible, as well as the image of the ‘macho’ man that is expected and applauded in men (always linked, of course, to sexuality) is not only false, but also puts brutal pressure on men.
So what happens if a man doesn’t feel like having sex? In therapy, I often meet men of varying ages who say they feel ‘less manly’ or are afraid of being judged, by women in the case of heterosexual relationships, but especially by other men.
How, then, does this fear of not having an insatiable desire affect them?
Firstly, performance anxiety sets in. Many of the men who say they have sex-related problems in consultation are very focused on ‘lasting’ or ‘wanting’ enough, but to please the other person, not to feel good about themselves. Similarly, these men will have difficulty expressing emotions that “prevent” or hinder sex or vulnerability during sexual relations, as this destroys that image of masculinity. And last but certainly not least, most of the cases of erection problems that I encounter in my practice are due to stress, either because of the two factors already mentioned or because of not paying attention to one’s emotional state at the moment of sexual intercourse (and if we are exhausted after a long day, feeling unwell or in a bad mood, we don’t feel like it, right?).
The reality is that the level of desire varies from person to person. Men can also have moments when their sexual desire fluctuates without this being a sign of a ‘lack of virility’ (or a lack of attraction to their sexual partner, which is also a very common fear).

Myth 2: ‘Women do not have as much sexual desire as men.’
This myth is doubly toxic: on the one hand, it repeats patterns that have been known and maintained for centuries of female sexual repression: it limits and can even punish female desire; on the other hand, it makes it invisible, hiding it even further in a secret or taboo realm. Furthermore, it limits access for a high percentage of women to sex education or the exploration of their own desire, since many women have learned (from hearing it) that it is ‘not right’ to desire, take the initiative, or talk about pleasure.
This idea can have a significant impact in several ways: firstly, we find ourselves in therapy with women who feel guilt or shame for feeling sexual desire or even for wanting to explore that desire (this may be alone, but it grows much more if it is done with several different sexual partners over time). We also hear stories of women who ‘hold back’ during sex, who do not show pleasure or communicate their desires to their partners for fear of being ‘too much’, which ends up creating a bad relationship with sex and can even lead to relationship problems.
Women, like men, have sexual desire. This sexual desire can be greater or lesser, and depends on various factors (emotional, circumstantial… just like in men, really). What often changes, and can reinforce this myth, are the ways in which it is expressed, which are also influenced by the cultural environment.
Myth 3: ‘Emotions do not affect sex.’
This idea is so widespread and has been reinforced so much in films and books that many patients in therapy overlook their emotional state when having relationships with other people. The lack of recognition of emotions can lead a large number of patients to believe that there is a physiological or psychological problem, when the reality is that they are simply not choosing the right moment.
It is quite logical to think that if we are tired, stressed, sad or angry, we cannot connect in the same way with people, plans or activities (even if we normally enjoy them). In sex, this happens in the same way: if we cannot generate arousal (because another emotion is already occupying that space) and connect with our sexual partner, the quality of the relationship can decline to the point of becoming impossible.
As in other aspects of life, emotions are inherent to human beings, so we cannot put them off, not even for sex. The reality is that the more emotionally available we are, the more we can connect with arousal, pleasure and trust with the other person, the better our sexual relationships will be.

Myth 4: ‘Sex should be spontaneous and perfect’
Can you imagine a life in which all sexual encounters were like those depicted in adult material or films? It would surely be an intense, exhausting, unrealistic… and frustrating experience. The belief that sexual relations should arise ‘naturally’ and ‘perfectly’ (what could be more natural than human interaction? What is perfect about sex if we are all different?) disconnects us from our needs and tastes. The key to enjoying good relationships is based on knowing yourself and your partner, communication and consent. Contrary to the belief that many people bring to counselling sessions: talking during sex is necessary. Communicating needs, tastes, preferences, asking for permission and much more only improves the connection between two people, aligning them for greater enjoyment (no, it doesn’t kill the mood).
If we communicate openly during sex, we can avoid having unrealistic expectations about what we should and should not do, let go of the fear of failing or that the other person will not enjoy themselves, and normalise expressing how we feel. With these three simple steps to building sex, there is no room for error.
Myth 5: ‘If there is love, sex will always be good.’
Although love and pleasurable, satisfying sex can go hand in hand (and patients often say they connect better sexually with people they have an emotional bond with), they are not two correlative conditions. The existence of a good emotional bond does not make us superhuman, it does not give us the power to know what is in the other person’s head, nor does it guarantee that we will always enjoy sex. The reality is that there are many variables beyond the emotional bond that can affect satisfaction with sexual relations.
If we entertain the idea that just because we love the other person, sex will definitely be satisfying, we may end up feeling guilty for not being satisfied or happy (if I love my partner, why am I not able to enjoy our relationship?), we may avoid talking to the other person about what is happening to us or what we need, and this can lead to relationship problems. In fact, if sex is always pleasurable in a relationship when there is love, why do many patients repeat that love and commitment are there, but the sexual aspect often falls short?
As with the previous myth, reality prevails: sex does not come out of nowhere, but is something that is worked on, including the emotional bond for a greater connection with the other person, but without neglecting the needs of each individual, even in the most loving relationships.

Myth 6: ‘Orgasm is the goal of sex’
When sex becomes a ‘race to orgasm,’ we lose sight of everything along the way, overlooking signs of discomfort or failing to enjoy the process. This idea that sex must culminate in orgasm in order to be satisfying brings with it various difficulties, such as generating anxiety if orgasm (and not only one’s own, but also that of the other person) does not occur, as well as a significant impact on self-esteem and perception of oneself and one’s abilities (sexual, physical and emotional) if the peak of pleasure is not reached. Furthermore, it can lead to the well-known self-fulfilling prophecy in therapy: our patients are so afraid and under so much pressure to achieve orgasm that it never comes (remember that emotions affect sex).
How can we feel better during sexual relations? How can we have pleasurable sex? The reality is that the goal of sex is not about reaching orgasm or not. The pleasure of physical sensations, of connecting with another person, of shared intimacy and of the other person’s presence define a satisfying relationship. There are many other things that come before or complement orgasm: kissing, caressing, playing, confessions, praise… orgasm can be part of it, but it is not the goal.
To recap, how do all these beliefs affect our psychological well-being?
Sexual myths are not just stories, they are part of the collective social imagination and impact the way we think, feel, act and even relate to others. Some of the most common symptoms we see in therapy are:
- Feelings of guilt or shame about what we desire or do not desire.
- Self-esteem affected by not fitting the mould of sexual perfection.
- Fear of making mistakes, of failure, anxiety about not doing what is ‘right’ and fear of rejection.
- Many problems in relationships due to lack of communication (leading to frustration, feelings of isolation, of not being understood, etc.).
Unlearning these beliefs in order to adopt more compassionate and adaptive ideas takes time, but it is possible. Here are some keys to get you started:
- Real sex education: Read, get informed, listen to professionals. Explore what you like in sex. Talk about it with other people, ask yourself questions. The more knowledge you have about your body, the better you will feel expressing your needs. The more information and neutrality we have towards sex, the more difficult it will be for those beliefs to have a negative impact.
- Talk without taboos: With your partner, with friends, in therapy. Talking about sex naturally is an act of mental and emotional health. Demystifying sex means normalising it. Normalising sex means talking about it openly, free of prejudice and free of shame.
- Consult with professionals: If you feel that your sexual relationships are being affected, do not hesitate to seek professional help. Sharing doubts or insecurities in a safe environment helps to eliminate feelings of loneliness and can offer new and kind perspectives for a better sex life.
- Question what you see: Remember that many of the images we consume in our daily lives (on social media, in adult material, in literature and cinema, even in conversations with other people) do not reflect reality. Before accepting a belief as true, take a moment to reflect and ask yourself if you feel that way, if this idea convinces you, what beliefs are linked to the main one (if sex is always good in a relationship, does unsatisfactory sex mean a lack of love?) and, if necessary, seek professional psychological/sexological help.

It is important not to experience sexuality from a place of guilt or demand. Each person has different experiences and needs, and myths are just invisible baggage that we carry around and end up weighing us down. Opening your mind to other realities is the first step to experiencing sex with more freedom, pleasure and mental health. There are many ways to experience good sex, but by feeding into unrealistic beliefs, we will find the same outcome: discomfort.
Frequently Asked Questions (FAQ)
1. Is it normal for sexual desire to fluctuate?
Yes. Sexual desire naturally varies depending on emotional, physical, and contextual factors.
2. Do emotions affect sexual performance?
Yes. Stress, sadness, or fatigue can influence arousal and connection with a partner.
3. Is orgasm necessary for sex to be satisfying?
No. Pleasure, intimacy, and emotional connection are also key components of satisfying sex.
4. Does love guarantee a fulfilling sex life?
Not necessarily. Sexual satisfaction requires communication, self-awareness, and mutual understanding.
5. When should I seek professional help?
If sexual concerns cause anxiety, guilt, relationship difficulties, or persistent emotional distress.
About the author
Clara Gallego is a general health psychologist at Sinews MTI. She specializes in couples therapy and trauma and attachment. She also treats other issues such as anxiety, grief, sexuality-related problems, family conflicts, and interpersonal relationship difficulties. Her approach is integrative, adapting the intervention to each patient, but with a clear systemic focus (the individual as part of a system). She also incorporates her knowledge of mindfulness and compassion into her interventions.
Sinews MTI
Psychology, Psychiatry and Speech Therapy

What to Do After a Child’s Autism Diagnosis: Questions to Navigate as a Family
In the past decade, autism spectrum disorder (ASD) diagnoses have tripled worldwide. About 1 in every 127 people is now recognized as being on the spectrum. We’re also learning more about how autism shows up differently in girls, leading to a faster rise in diagnoses among females. Although the average age for diagnosis is around 5 years old, more adolescents and adults are now receiving a diagnosis later in life.
When your child receives an autism diagnosis, it can stir up a mix of emotions: relief at finally having some answers, fear of what lies ahead, and confusion about what this label truly means. As a parent, you might wonder: Does this diagnosis really capture who my child is? Will it help us understand their unique strengths and provide the support they need?
What is autism?
Autism is a neurodevelopmental condition. This means it involves differences in how the brain develops and processes information over time. These differences can affect how a person communicates, interacts socially, and understands the world around them. For some children, this might mean challenges with expressive language. For others, it might show up as sensory sensitivities or a strong need for routines, making unexpected changes difficult.
As my colleague Ana Pilar Collado recently explained, calling it a spectrum better reflects what we now understand: autism appears in many diverse ways. The word spectrum is key because no two autistic people are exactly alike. This broader understanding has allowed many people—especially girls and adults—who were previously undiagnosed to finally receive recognition and support.
You may ask yourself: How can one diagnosis cover such a wide range of needs?

What level of support does my child need?
To accurately reflect autism’s many different presentations, the DSM-5 diagnostic manual includes three levels based on the amount of daily support a person requires:
- Level 1 – Requires support: These individuals are often autonomous and verbal but face challenges with social communication or flexible thinking. They usually need support managing social relationships, changes, or highly stimulating environments.
- Level 2 – Requires substantial support: These children have more noticeable difficulties in communication and behavior, requiring more structured daily support.
- Level 3 – Requires very substantial support: These individuals need constant help with communication, daily activities, and safety. Often, autism is accompanied by intellectual disability or significant developmental delays.
What about IQ, intellectual disability, and Asperger’s syndrome?
One common question families ask is: Does an autism diagnosis mean my child has an Intellectual Disability? The answer is: not necessarily. Autism and intellectual ability are related but not the same. Some autistic people do have Intellectual Disabilities (significant challenges with learning and reasoning), but many do not.
Approximately:
- 40% of autistic individuals have an IQ below average (less than 85),
- 40% have an above-average IQ (more than 115),
- and 20% fall within the average range.
These figures show how diverse autism is—not only in behavior and personality but also in cognitive ability.
You may have also heard of Asperger’s syndrome, especially if you’ve talked with adults diagnosed during childhood or adolescence. Asperger’s was recognized in 1994 but was removed from the DSM-5 in 2013. It was used to describe people on the spectrum with strong language and cognitive skills but difficulties in social, sensory, or behavioral areas. Over time, Asperger’s became popularly associated with “high IQ” or being “gifted,” leading to a common misconception: if someone is intellectually capable, they don’t need support.
In reality, intellectual ability alone doesn’t determine what kind or amount of help a person needs. Someone can excel academically but still struggle with everyday tasks, social relationships, anxiety, or overwhelming environments. That’s why the DSM-5 replaced subtypes like Asperger’s with a spectrum diagnosis and support levels—better reflecting real life and ensuring everyone can access the help they need.
Because traits, intellectual ability, and support needs overlap in complex ways, your child’s diagnosis likely included both autism-specific assessments and a cognitive evaluation. Structured interviews and questionnaires help professionals understand your child’s strengths and challenges across different settings. This holistic view goes beyond labels and helps create personalized support plans tailored to who your child really is—not just test scores.

What’s the point of the diagnosis? What are its benefits?
If diagnosis is about understanding your child’s unique needs and strengths, you might ask: Why use a general label like Autism Spectrum Disorder? This is an important question. Diagnosis is not meant to box anyone in but to open doors—to services, support, and understanding within your community. Receiving a formal autism diagnosis is helpful for several reasons:
- Access to resources and supports: Many therapies, accommodations, or academic aids require an official diagnosis. Without it, families often hit roadblocks trying to get help.
- Guidance for interventions: The diagnosis helps professionals and caregivers use specific knowledge and tools tailored to autism—such as speech therapy, occupational therapy, social skills training, or school accommodations. Interventions are always customized, but diagnosis guides the general approach.
- Shared language: Naming what’s happening makes it easier for families, teachers, health professionals, and the child to communicate. It explains behaviors that might otherwise be misunderstood or judged.
- Validation and relief: For many, diagnosis brings comfort. It confirms what families have observed and shifts the focus from “something’s wrong” to “my child experiences the world differently, and now we understand why.”
- Belonging and identity: Over time, many autistic people and their families find the diagnosis offers not just support but also a sense of identity. It can connect them to communities with similar experiences, fostering belonging. For children, especially as they grow, understanding autism can be freeing rather than limiting.
In short, an autism diagnosis isn’t the end—it’s the start of a more informed, compassionate, and individualized journey.
What steps come after the diagnosis?
- Give yourself time to process: It’s okay to feel many emotions—relief, sadness, confusion, hope—or all at once. Allow yourself space to absorb what this diagnosis means for your child and family. Remember: the diagnosis doesn’t change who your child is; it changes how you understand their experience.
- Ask questions: Don’t hesitate to reach out again to the professional who made the diagnosis. You might ask:
- What does this diagnosis mean for my child specifically?
- What are their strengths and current challenges?
- What supports or interventions do you recommend now?
- Explore support and services available: Usually, after diagnosis there are one or more guidance sessions with the evaluating professional to answer questions, share feelings, and begin planning. Support is not just for your child but for the whole family.
- Coordinate with the school: An official autism diagnosis often opens doors to educational resources and specialized support like special education teachers or speech therapists. You can start by meeting with your child’s teacher and the school counselor, who coordinates support and evaluates needs. They can advise you on available services and help develop an individualized plan that evolves as your child grows. Your psychologist can also share reports or recommendations to better adapt the school environment.
- Learn about autism (but take it slow): It’s tempting to try to understand everything at once, but autism is a broad and evolving topic. Trust professionals and experienced families to guide you to good books, websites, or parent groups. Learning little by little will help you feel more confident and less overwhelmed.
- Connect with other families: Talking to other parents who’ve been through similar experiences can be very comforting and practical. Many find emotional support and useful ideas through these connections.
- Focus on your child, not just the diagnosis: Most importantly, the diagnosis doesn’t define your child. It helps explain some behaviors, preferences, and needs, but remember to keep seeing your child as a whole person—with their interests, humor, creativity, and unique way of being. Support plans should revolve around who they are, not just the label.

About the author
Iciar is a Psychologist at SINEWS MTI and PhD student. She specializes in neuropsychological assessment, diagnosis, and intervention across neurodevelopmental conditions such as autism and ADHD. Her doctoral research focuses on emotion regulation and its impact on social coping and quality of life in neurodiverse youth. Iciar works with clients of all ages and backgrounds, addressing a broad range of mental health concerns including anxiety and behavioral challenges. Her approach is integrative and strength-based, emphasizing personalized care that respects neurodiversity and promotes wellbeing. Drawing from her international training and clinical experience, she combines research and practice to support families in understanding and accompanying their children’s unique developmental journeys.
Sinews MTI
Psychology, Psychiatry and Speech Therapy

How Stress Affects Physical Health
Stress is a natural response that occurs in our body when facing situations that pose a threat or a challenge. However, when stress becomes chronic, it can have devastating effects on our physical health. The purpose of this article is to explore the effects of stress on our body and its possible long-term consequences. Additionally, we will include some strategies to manage it effectively.
What is Stress?
According to the RAE, stress is defined as «tension caused by overwhelming situations that lead to psychosomatic reactions or psychological disorders, sometimes severe.» Stress can affect anyone, regardless of age, body type, gender, etc. When it is prolonged or excessive, it can negatively impact both mental and physical health. From a psychological perspective, stress is not only experienced emotionally but also influences the body’s functioning in various ways. However, it is important to distinguish between the different types of stress we may experience:
Acute Stress
This is the most common type and occurs as an immediate response to a stressful event or situation. It is usually short-term and can be triggered by specific situations such as taking an exam, a job interview, or an important public presentation. It is characterized by symptoms such as heart palpitations, sweating, increased muscle tension, and intense emotions like anxiety or anger. Acute stress can be useful as it activates the body and mind, but if it becomes too intense, it can lead to fatigue and emotional problems in the long run.
Episodic Acute Stress
This occurs when a person frequently experiences episodes of acute stress in their daily life. Individuals with this type of stress often face constant or repetitive challenges in their routine. Those who suffer from it may always feel «on edge,» experiencing emotions such as irritability, anxiety, or frequent mood swings. The impact of this type of stress can lead to health problems such as hypertension, chronic migraines, digestive disorders, or sleep difficulties.

Chronic Stress
This type of stress lasts for long periods and is usually associated with situations perceived as uncontrollable, unsolvable, or beyond one’s control. Symptoms can include emotional exhaustion, a depressive state, lack of motivation, and more chronic health problems. Chronic stress is the most harmful, as it has prolonged effects on both body and mind, increasing the risk of heart disease, depression, anxiety, and other conditions.
Traumatic or Post-Traumatic Stress
This occurs in response to traumatic events that endanger a person’s life or physical and emotional integrity, such as witnessing severe accidents, natural disasters, or experiencing physical or psychological violence. This type of stress is associated with Post-Traumatic Stress Disorder (PTSD). It can include severe anxiety symptoms, intrusive memories of the event, nightmares, hypervigilance, and flashbacks with intense physical reactions when recalling the event.
The Mechanism of Stress and Its Impact on the Body
When facing a stressful situation, our brain activates the hypothalamic-pituitary-adrenal (HPA) axis, releasing hormones such as cortisol and adrenaline. Why are these substances useful? When secreted by the brain, they prepare us for a «fight or flight» response, triggering bodily reactions such as increased heart rate, blood pressure, sweating, etc. This mechanism helps us in moments of danger or alert. However, if it remains constantly activated, it can cause significant health damage.
Stress also affects our prefrontal cortex, the region of the brain responsible for decision-making and emotional regulation. In cases of chronic stress, this area may become less effective, making it harder to manage emotions and solve problems efficiently.

How Does Stress Affect Our Bodies?
Our body consists of twelve systems that help coordinate and integrate its functionality. Stress can impact these systems, leading to damage that affects physical health:
- Cardiovascular System: Chronic stress can cause high blood pressure, arrhythmias, and an increased risk of heart disease. Prolonged exposure to cortisol contributes to arterial inflammation and hardening. Additionally, stress can increase cholesterol levels, raising the risk of atherosclerosis or coronary diseases.
- Immune System: High and sustained stress levels can weaken the immune system, increasing susceptibility to infections, delaying wound healing, or worsening autoimmune diseases.
- Digestive System: Stress can cause numerous digestive problems such as irritable bowel syndrome, gastritis, and gastroesophageal reflux. It also affects gut microbiota, impacting overall body balance. In some cases, it can lead to eating disorders such as anorexia or binge eating, affecting both physical and mental health.
- Endocrine System and Metabolism: Excessive cortisol release can alter blood sugar levels, promoting the development of diabetes. It can also contribute to weight gain. Additionally, stress interferes with appetite regulation, leading to unhealthy eating behaviors.
- Musculoskeletal System: Stress causes frequent muscle tension, leading to headaches, muscle stiffness, and general discomfort. Over time, this can result in chronic conditions such as fibromyalgia or musculoskeletal disorders. Prolonged muscle tension can also contribute to posture problems and reduced mobility.
- Mental and Emotional Health: While the main focus is on physical impact, we cannot ignore that stress is closely related to psychological issues such as anxiety and depression. Constant exposure to high stress levels can alter the production of neurotransmitters like serotonin and dopamine, essential for emotional well-being.

The Role of Psychology in Stress Management
From a psychological perspective, numerous strategies have been developed to cope with stress in a healthy way with the help of psychologists who guide their application. Some of the most effective include:
- Relaxation techniques: Meditation, diaphragmatic breathing, or mindfulness can help reduce nervous system activation and promote a state of calm. Studies show that regular practice of these techniques can lower cortisol production and improve immune function.
- Physical exercise: Engaging in regular physical activity helps reduce cortisol levels and release endorphins, improving mood and stress resilience. Exercise also aids in sleep regulation, which is essential for body functionality.
- Social support: Maintaining healthy social relationships and having a support network can help manage stress-related difficulties and reduce its perception. Positive social interactions stimulate the release of oxytocin, a hormone that promotes relaxation and well-being.
- Cognitive restructuring: Identifying and modifying negative thought patterns can change how we face stressful situations. This technique, commonly used in therapy with the help of a psychologist, helps individuals develop a more adaptive and less catastrophic perspective on stress.
- Psychological therapy: Cognitive-behavioral therapy (CBT) and Acceptance and Commitment Therapy (ACT) have proven effective in improving stress management and reducing its impact on patients' health.
- Sleep regulation: Good sleep is essential for physical and mental recovery. Establishing a proper sleep routine and reducing screen exposure before bedtime can improve sleep quality and lower stress levels.

Stress is a natural and necessary response for survival, but prolonged exposure over time can lead to serious physical and mental health issues. Understanding the effects of stress and applying appropriate management strategies can significantly improve quality of life and prevent severe health conditions. The balance between mind and body is essential for overall well-being, and learning to manage stress is key to leading a healthy life. Achieving this requires combining psychological strategies with healthy lifestyle habits that promote general well-being.
About the author
Lidia Fernández
Sinews MTI
Psychology, Psychiatry and Speech Therapy

How Can Cognitive Behavioural Therapy (CBT) Assist Me? Unravelling the Maze of Thoughts
Imagine waking up each morning overwhelmed by a cloud of dread about the day ahead. You’re trapped in a vicious cycle of negative thoughts, each feeding into the next, building a formidable barrier between you and peace of mind. Whether it’s stress from work, anxiety about future uncertainties, or a lingering sadness that taints your enjoyment of life, finding a pathway to psychological well-being might seem akin to navigating a maze without a map.
So, what can you do? How can you break this cycle when you’re aware that your actions might be detrimental, yet you’re unsure of the alternatives? This is where Cognitive Behavioural Therapy (CBT) can make a significant difference.
What is Cognitive Behavioral Therapy?
CBT is a robust form of psychological treatment proven effective for a range of issues including depression, anxiety disorders, alcohol and drug misuse, marital problems, eating disorders, and severe psychological conditions. Extensive research demonstrates that CBT significantly enhances functioning and quality of life. It operates on the fundamental principle that our thoughts, feelings, and behaviours are interconnected, and that altering negative thought patterns can affect changes in both feelings and behaviours, and that changing behaviours can alter our feelings and negative thought patterns.
How Cognitive Behavioral Therapy Works
Many people associate therapy with lying on a couch, discussing one’s mother and traumatic past, receiving only nods or «mhms» from the therapist. However, encountering a CBT session can be quite a revelation, as it differs significantly from these traditional notions of psychotherapy. CBT sessions are interactive, practical, and structured. They focus on specific problems and offer direct tools and techniques to manage and overcome these problems. In CBT, the therapeutic process is normally divided into three key phases:
- Assessment: This initial phase involves a detailed examination of the client's problems. The therapist and client work together to identify specific problem areas. This could include understanding the situations, thoughts, and behaviours that lead to difficulties in the client’s life.
- Analysis: In this phase, there is a deep dive into understanding why these problems exist. The therapist helps the client to uncover patterns of thinking or behaving that contribute to their distress. This involves looking at how certain thoughts or behaviours are unhelpful, and exploring their origins and impacts.
- Intervention: This is the action phase, where strategies and techniques are applied to modify the problematic thoughts and behaviors. The interventions are practical exercises and tasks that the client undertakes, both within and outside of therapy sessions. These might include exposure therapy, thought records, or behavioural experiments.

For example, Ginny has sought therapy because she struggles to participate in social situations. Her job involves many important social events, and she has noticed that her inability to partake is affecting her relationships with her colleagues. She absolutely hates this and does not know how to stop being so afraid. She tried to go once. She prepaid and got ready to leave, but taking the step to leave her apartment proved too difficult, so she decided that Netflix and a glass of wine would be a better way to spend her evening, even though it felt terrible not to have been able to go.
- Assessment: The therapist and Ginny discuss everything she has been feeling, thinking, and doing when confronted with social situations to explore possible explanations for why it is too difficult to make the leap. They explore both the past and the present to understand.
- Analysis: When the CBT therapist understands what is going on, why Ginny started to struggle and why she is still struggling today, this information is shared and discussed between them. This is crucial because understanding the situation makes it easier to determine what needs to change. They do not want to guess how to intervene; they want to know.
- Intervention: Now it is time to make some changes. Ginny realizes that she anticipates a lot of negative scenarios that might occur if she goes to the party: “What if I say something weird?”, “What if my clothes are too formal or informal?”, “What if nobody talks to me, or they are bored when they do?” Her therapist helps her challenge these thoughts and prevent them from dictating her behaviour. Then, together, they create a plan to expose Ginny to what she fears the most, equipping her with all the necessary tools to manage the situation effectively.
The process of CBT is highly collaborative. Both the therapist and the client have active roles in the therapy sessions and in the work done between sessions. This collaborative effort helps to empower the client, making them an active agent in their process of change, also giving them the tools on how to manage problems in the future without the need of a therapist.
Moving Beyond the Past
While our past is crucial as it shapes who we are today, dwelling on it can impede our progress. CBT helps clients focus on the present and future, learning from the past but not being anchored by it. We discuss the past to understand our learning and experiences but shift focus to current actions and forward-looking strategies.
Benefits of Cognitive Behavioral Therapy
One of the key benefits of CBT is that it is short-term and goal-oriented, typically lasting anywhere from a few weeks to several months. We do not want to suffer longer than necessary! This does not mean the benefits are fleeting; rather, the changes are designed to be long-lasting. CBT provides clients with tools and techniques that are not just about coping in the moment but are skills that clients carry with them for life. This approach ensures that individuals do not have to rely on continuous therapy but can manage independently, reducing the likelihood of future relapses. The benefits of CBT include:
- Evidence-Based: CBT's effectiveness is backed by substantial research, making it a reliable form of therapy for various psychological problems.
- Skill Development: Clients acquire valuable life skills that enable them to effectively tackle a variety of life's challenges. These skills, learned within the therapy setting, can be generalised to address similar issues that may arise in the future.
- Sustainability: While the therapy itself is often short-term, the tools and strategies learned are enduring, helping ensure that the improvements are maintained long term.

Embracing Negative Emotions
Even though CBT talks a lot about change, it is essential to acknowledge that feeling bad is sometimes necessary. Negative emotions are a normal part of life; they teach us resilience and give context to our happiness. How would we recognise joy if we never experienced hardship? How would we handle danger without fear? Thus, not every problem requires therapy – many challenges can be managed on our own, even though we feel bad in the moment. However, when these issues persist and begin to impact our daily lives significantly, seeking therapy may be the appropriate step to take, and this is when CBT would be able to help us.
Sinews MTI
Psychology, Psychiatry and Speech Therapy

Evolution of Transsexuality-Related Diagnoses
DISCLAIMER: This article contains obsolete language that stems from the pathologization of realities that in no case are considered disorders by any reputable Psychology or Psychiatry institution, both at a national and international level. The language used in this article reflects the evolution of academic and health institutions throughout history and it is included here to reflect how the approach of institutions to social demands influences the categorization of the realities studied.
This article is a continuation of the one I recently published on the historical evolution of the diagnoses that the American Psychiatric Association attributed over the years to people with a non-normative sexual orientation. That is, with a sexual orientation other than heterosexuality.
The previous article would not make much sense if I did not also publish this one right after it, as the goal behind writing both of them is to observe how the evolution of the different diagnoses that have been assigned to people with non-normative sexual orientations is surprisingly similar to that of diagnoses assigned to trans people.
Evolution of Transsexuality-Related Diagnoses in the DSM Manuals of the American Psychiatric Association
As in the previous article, I will now review the different diagnoses that the American Psychiatric Association has assigned to trans persons throughout the different editions of the DSM.
DSM-I (1952)
The first edition of the DSM does not explicitly mention transsexuality.
DSM-II (1968)
DSM-II proposes a category for Sexual Disorders, although it is limited and mostly focused on homosexuality and other “disorders of sexual deviance”. Transsexuality is not separated from other realities, but different forms of gender role nonconformity were broadly encompassed as Sexual Deviance.
DSM-III (1980)
DSM-III represented a significant change by introducing for the first time the term “Gender Identity Disorder” (GID), defined as a persistent incongruence between biological sex and the person’s experienced or expressed gender identity. This was an early attempt to formally recognize transsexuality within a clinical framework.
The diagnosis of GID was classified under a new chapter called “Psychosexual Disorders,” which also included other disorders related to sexuality. However, this classification was criticized for pathologizing gender identity not congruent with the sex assigned at birth.
DSM-III-R (1987)
In the revised version of DSM-III (DSM-III-R), the diagnosis of Gender Identity Disorder was maintained, but some modifications were made to the diagnostic criteria. Transsexuality was still seen as a mental disorder.
DSM-IV (1994)
In DSM-IV, Gender Identity Disorder is retained, but distinctions are added for evaluations in children, adolescents and adults. This category caused controversy because of the implication that gender variants in childhood were seen as pathological.
DSM-IV-TR (2000)
The DSM-IV was revised in 2000. The diagnosis of “Gender Identity Disorder” was maintained with some modifications, maintaining the categories and criteria established in the previous version. The manual was still under criticism from the trans community and activists for continuing to include trans realities within pathologizing labels.
DSM-5 (2013)
The publication of DSM-5 marked a major shift in how the American Psychiatric Association addresses transgenderism. The term “Gender Identity Disorder” was replaced with “Gender Dysphoria.” This change is exposed as an effort to reduce the stigma associated with the diagnosis by emphasizing that it is not the gender identity itself that is problematic, but the significant distress that a trans person may experience in the current context.
In addition, the DSM-5 introduced more detailed diagnostic criteria, differentiating gender dysphoria in children from that experienced in adolescents and adults. It was also explicitly recognized that not all people with gender incongruence experience significant dysphoria, in order to clarify that transsexuality is no longer inherently viewed as a mental disorder.
DSM-V-TR (2022)
The DSM-5-TR (Diagnostic and Statistical Manual of Mental Disorders, Revised Text) represents a revision of the DSM-V, adding minor changes to the 2013 edition, including some key changes regarding gender dysphoria to reflect greater accuracy and awareness of the social reality being discussed:
- The term “desired gender” has been replaced with “experienced gender,” underscoring that gender identity is an internal experience and not just a desire for change.
- The phrase “medical cross-sex procedure” has been updated to “gender affirming medical procedure,” reflecting a more respectful and affirming approach toward medical interventions related to gender identity.
- Language regarding sex assigned at birth has been modified. The terms “natal male” and “natal female” are now described as “person assigned male at birth” or “person assigned female at birth,” reinforcing the distinction between assigned sex and experienced gender.
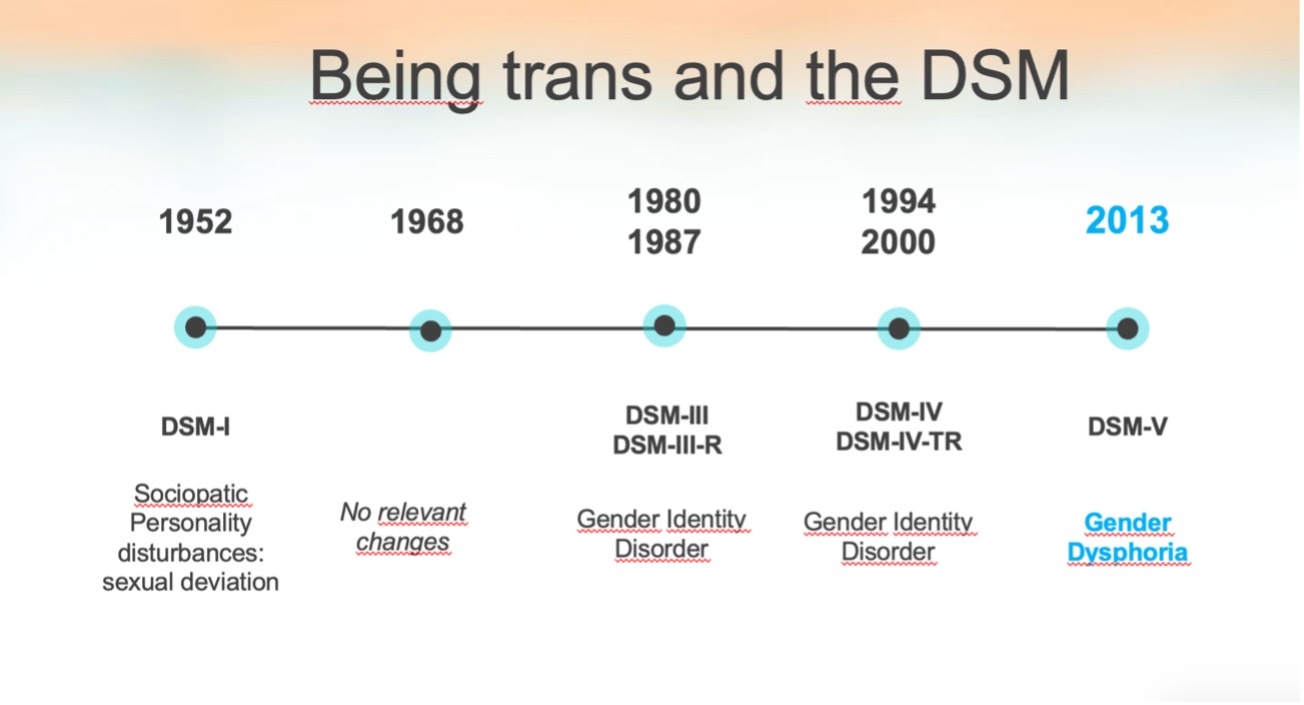
Future Perspectives
The evolution of transgender-related diagnoses in the DSM manuals reflects an ongoing process of revision and updating as understanding of gender diversity advances. It is expected that future revisions will continue to depathologize trans identities and focus more on providing a supportive framework for those experiencing gender dysphoria, rather than classifying them within a pathological context.
The current category of “Gender Dysphoria” is not without controversy as it receives similar criticism as the category of “Egodystonic Homosexuality” did at the time. There are also arguments, of a more practical nature, in favor of it because of the requirement of insurers and health services for the presence of a diagnosis that justifies gender reassertion interventions in trans persons. However, some argue that there are already natural conditions, such as pregnancy, that require medical interventions without the need for a pathologizing diagnosis, so the same logic could be applied to interventions aimed at improving the quality of life of trans people.
About the author
Jorge Jiménez Castillo is a psychologist at SINEWS, where he practices in English and Spanish. He works daily with local and international populations and has a long history of studying the reality of the LGTBIQ+ community in and out of the clinic. He works from a cognitive-behavioral approach with evidence-based interventions and believes that in order to provide quality psychological care one must be aware of the inequalities that intersect with users and explore how they intersect with each other.
Sinews MTI
Psychology, Psychiatry and Speech Therapy

The journey to clear communication: Improve your accent
Communication is the expression of a message by speaking, writing, or signing. When a message is not expressed clearly, it can be misinterpreted. Clear communication means that the receiver of the message understands exactly what the sender is intending. It is essential for being understood, building relationships, and communicating efficiently.
For many Spanish speakers, having clear communication when speaking English can be an important step when it comes to achieving their goals, whether that be in their careers, their social lives or just not having to repeat themselves and being understood. The purpose of accent training is to help you feel confident and to communicate as effectively as possible—not to sound like a native speaker or erase your individuality. This in-depth guide will go over what accent training is, how it works, and how one-on-one coaching can help with clarity, confidence-building, and successful communication in both professional and social settings.
What is Accent training?
Accent training is personalized coaching that helps individuals who want to address specific communication challenges. It focuses on pronunciations, appropriate intonation, rhythm, timing, and stress patterns. It helps speakers identify which habitual features they take from Spanish and use while speaking English. The goal of accent training is not to sound like a native speaker, it is to help individuals communicate clearly and confidently. Accent training is flexible and personalized to meet each individual’s needs.

What are accents?
Accents are made up of substitutions; the sounds, rhythms, and intonations from a person’s native language or region that he or she uses when speaking English. If these substitutions are not what the listener expects to hear in English, the listener hears an accent (The accent channel). Accents are a normal part of any language and reflect the cultural diversity of speakers. No accent is better than another; they are all valid forms of expression.
Accents only become noteworthy if they begin to interfere with someone’s communication at work or in social settings. They may cause confusion or prevent someone from achieving their goals. Some people may also feel that there are preconceived notions about their accent, which can lead to biases and stereotypes. The choice to change the way we speak is up to each individual. They may want to improve their communication and avoid embarrassing speech mistakes.
After accent training, most accents become difficult to associate with any specific location; they begin to sound very neutral and unidentifiable. Speakers become easily understood, which boosts their confidence and allows them to communicate clearly and as effectively as possible.
Benefits of Accent Training:
- Aids in clearer communication and pronunciation.
- Helps individuals work towards their career, social network, and life goals.
- Increases confidence and self-esteem.
- Reduces linguistic bias and discrimination.
- Improves customer satisfaction.
- Enhances listening skills.
- Expands professional opportunities.
- Nurtures better social integration.
- Increases cultural sensitivity and the ability to connect with diverse backgrounds.
- Improves credibility in professional settings.
- Decreases stress levels associated with speaking in a foreign accent.
- Enhances academic performance for students by facilitating participation in discussions and presentations.
- Strengthens personal relationships by reducing misunderstandings and fostering clearer interactions.
- Empowers individuals by giving them a sense of control over their communication and self-presentation.

Why personalized training instead of apps and videos?
Personalized accent training provides many advantages over apps and videos. It offers immediate feedback and allows the opportunity to correct mistakes instantly. It also helps the individual to recognize their personal challenges when communicating; not every Spanish speaker has to work on the same objectives during accent training. Unlike apps and videos, personalized training is tailored to each individual’s needs. Working with a speech trainer also ensures you are accountable and practicing consistently, which is important for progress. Immediate feedback from a speech trainer is much more effective and leads to better results.
The accent training process
The process of accent training begins with a speech assessment in order to identify the sound substitutions, rhythms, stress patterns, and intonations that are currently being used and would need to be replaced with those of the goal accent (General American English for example). Once the substitutions are identified, appropriate objectives can be set. It is important to note that new objectives may appear after the initial assessment as the speech trainer is constantly assessing their client as they work together. Each session targets a single objective and consists of a variety of tasks that are practiced multiple times. During these tasks, immediate feedback is given to help the client identify any substitutions and make the necessary corrections. In addition to these in-session practices, at-home tasks are assigned; it is crucial that the client practices consistently outside of sessions in order to make notable progress. Repetition is necessary for making adjustments in the accent, and frequent practice is required for permanent improvement. The goal of accent training is for the client to internalize the correct speech patterns and produce them fluently in a way that is easily understood by their listeners.
How long will it take?
Each goal takes approximately one session to be taught. It is recommended to have one session a week, and normally takes between 12-15 sessions to work through each objective (depending on the number of objectives of each student, could be more, could be less). It is important that the student is practicing at home at least 15 minutes a day to make notable progress. After the completion of their program, the client will have the option of maintenance sessions if they would like to continue practicing with a speech coach.

What will we work on?
To communicate clearly and confidently, we will focus on several key areas tailored to each client’s needs. We will address high-value sounds specific to English that are uncommon in Spanish and can lead to pronunciation difficulties. We will also work on rhythm and stress; English features vary in syllable length, some syllables are stressed and longer, while Spanish syllables are generally given equal time. Additionally, we will focus on vocabulary, predominantly common words used in daily life that are often mispronounced. We will use targeted exercises and practice to improve pronunciation, rhythm, and vocabulary, which will enhance overall communication skills.
Taking action to overcome communication challenges is an important step towards personal and professional development. Accent training is a powerful tool that can help you achieve effective and clear communication. It can help boost your confidence and enhance your interactions in all areas of life. Working with a speech trainer provides you with personalized guidance and support, and ensures that you reach your goals more effectively than through self-study tools alone.
About the author
I am Jarrisvette Villarreal, originally from South Texas. I have been living in Spain for several years, where I have worked as an English teacher and have taught young Spanish speakers. Through my experience, I have become familiar with the common mispronunciations and typical mistakes Spanish speakers make when speaking English. In addition to teaching, I have experience as a Speech-Language Pathologist Assistant, working with children on articulation through speech therapy. I have also completed a specialized training in accent coaching through “The accent channel”, which has equipped me with the skills to provide personalized accent training. I have also worked diligently to achieve a neutral English accent; I understand the challenges and preconceived notions about having an accent. I am passionate about teaching pronunciation and excited to help others reach their communication goal.
Sinews MTI
Psychology, Psychiatry and Speech Therapy

How to Prepare Our Children for Life's Ups and Downs
What wouldn’t we do to protect our children, our most precious treasures? As parents, our instinct is to shield them from harm and negative experiences, fearing that difficult situations might cause pain or lasting trauma. We are driven by love and a deep desire to see our children happy and thriving. However, in our efforts to safeguard them, we might unintentionally prevent them from developing the resilience they need to navigate life’s inevitable challenges.
The Importance of Facing Challenges
Resilience is the ability to bounce back from adversity and cope with setbacks. It is a crucial skill that helps children manage the complexities of life. Shielding them from every challenge can leave them unprepared for future difficulties. Without encountering adversity, they may struggle to handle setbacks when they arise, potentially leading to a lack of confidence and problem-solving abilities.
Understanding and Accepting Emotions
One of the most valuable lessons we can teach children is that emotions—both positive and negative—are a natural part of life. Everyone experiences anger, frustration, or sadness at times, and that’s okay. Emotions are natural responses to situations and are not something we can directly control, but we can control how we express and respond to them.
It’s essential for children to understand that feeling sad, frustrated, or angry is perfectly normal. These emotions aren’t to be feared or avoided; rather, they are signals that deserve attention. For example, fear can alert us to danger, such as encountering a wild animal (we do not want to meditate when a lion is approaching us), prompting us to take protective action. Anger, when managed properly, can help us stand up for ourselves and advocate for a just world (we do not want to be taken advantage of). By teaching children to accept their emotions, rather than suppress or ignore them, we help them develop an understanding of their emotional responses—a cornerstone of resilience.
Teaching Healthy Emotional Expression
While understanding emotions is crucial, it’s equally important for children to learn how to express them in healthy and constructive ways. We cannot always run away from what scares us, nor can we lash out when angry. It is okay to feel emotions, but how we express them matters. Children need to learn effective ways to manage their emotions so they do not create new problems, which could intensify their negative feelings.

How Can I, as a Parent, Teach My Child to Cope with Negative Emotions Without Causing Trauma?
First, remember that your child is a keen observer. One of the most powerful ways they learn is by watching your behavior. If you model healthy emotional expression, your child is likely to emulate it. Conversely, if you respond to anger by hitting or breaking things, it becomes difficult for the child to understand that these behaviors are unacceptable.
A helpful guideline is to focus on teaching your child what to do, rather than what not to do. Instead of saying “Don’t hit” or “Don’t scream,” guide them toward alternative behaviors. For example, you might say, “I see you’re angry because of what happened. It’s understandable—it’s not fun when things don’t go your way. When you’re angry, use your words to tell me what’s bothering you, and we can figure out how to make things better.” This approach is easier said than done, especially when parents are short on time and energy. Many of us weren’t taught how to manage our own emotions, so learning to do so may be necessary before we can effectively teach our children. Remember, just like on an airplane, you need to put on your own oxygen mask before helping others.
Here are some strategies to help children manage and express their emotions effectively:
- Model Healthy Emotional Expression: Children learn by observing the adults around them. Demonstrate healthy ways to express emotions, such as calmly discussing what’s bothering you instead of yelling. This shows children that emotions can be managed without resorting to negative behaviors.
- Encourage Open Communication: Create an environment where your child feels safe to talk about their feelings. Encourage them to express what they’re feeling and why without fear of judgment. Listening actively and empathetically to their concerns helps them process emotions and strengthens their ability to communicate effectively.
- Teach Problem-Solving Skills: When children face challenges, guide them in thinking through possible solutions rather than stepping in to fix the problem for them. Encourage them to consider different approaches and evaluate potential outcomes. This builds their confidence and empowers them to tackle challenges independently.
- Set Healthy Boundaries: While all emotions are valid, there are appropriate ways to express them. Set clear boundaries around acceptable behaviors and help children find constructive outlets for their emotions, such as talking or engaging in physical activities.

Preparing Children for a Resilient Future
Building resilience in children doesn’t mean exposing them to unnecessary hardships; rather, it means equipping them with the tools they need to handle the challenges they will inevitably face. By teaching them to understand, manage, and express their emotions, we prepare them for the realities of life and help them build the resilience needed to thrive.
Resilient children are better equipped to cope with adversity, recover from setbacks, and continue moving forward. They understand that emotions are a natural part of life and that challenges, while difficult, can be managed. With these skills, they will be prepared to handle criticism at work or navigate conflicts in their personal relationships, confidently facing whatever life throws their way.
Sinews MTI
Psychology, Psychiatry and Speech Therapy